Skip to content

Advance directive and living will

Record your medical wishes and name a trusted person to speak for you if you cannot.

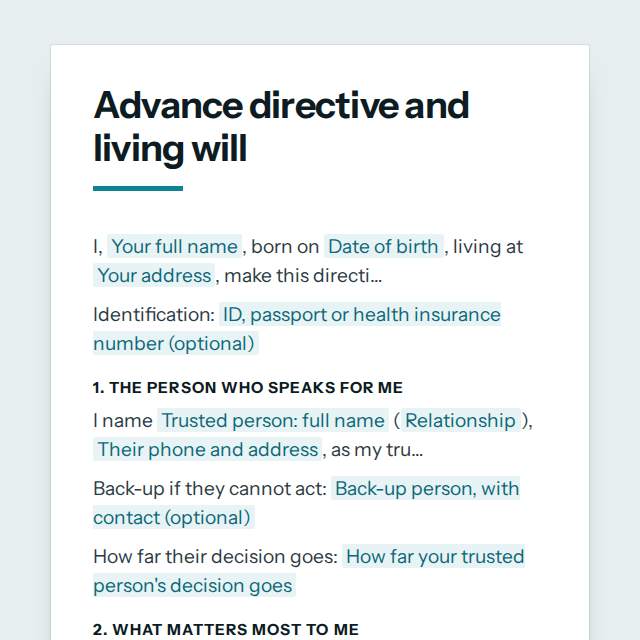
Advance directive and living will template, first page

Fill it in and preview

Advance directive and living will

I, Marie Dubois, born on 30 April 1958, living at 8 rue Victor Hugo, 69003 Lyon, France, make this directive while I am an adult of sound mind and free to decide. It applies if I become unable to understand, decide or tell others what I want about my medical care, for example because of serious illness, injury, unconsciousness or dementia.

Identification: 2 58 04 69 123 456 78

1. The person who speaks for me

I name Claire Dubois (daughter), +33 6 12 34 56 78, 5 place Bellecour, Lyon, as my trusted person. They may talk with my doctors, receive my medical information, and speak for me about my care.

Back-up if they cannot act: Paul Dubois, son, +33 6 98 76 54 32

How far their decision goes: They must follow my written wishes below, and decide only what they do not cover.

2. What matters most to me

Being at home, recognising my family, not being in pain, and keeping my dignity.

3. My choices about treatment

My choices below apply when I cannot decide for myself and I am in any of these situations:

  • I have an illness that cannot be cured and is expected to cause my death

  • I am permanently unconscious, with no reasonable hope of waking

  • I have severe dementia and can no longer recognise my family

  • Resuscitation (CPR): I do not want this

  • Breathing machine: Only for a trial period, to be stopped if it does not help

  • Artificial feeding and fluids: I do not want this

  • Antibiotics for a life-threatening infection: My trusted person decides

  • Treatments that only prolong dying: My trusted person decides

Where I have said that I do not want a treatment, I refuse it even if my life is at risk or may be shortened as a result.

If I am pregnant: I want the treatment needed for the safe birth of my child. After the birth, my choices above apply again.

In my own words:

If I have an illness with no hope of recovery, or I permanently cannot recognise my family, I do not want to be kept alive by a machine, but I want my pain and distress treated fully, even if that shortens my life.

4. Pain relief and comfort

Give me whatever medicine is needed to keep me comfortable, even if it makes me sleepy.

I want my pain and distress treated, and to be treated with dignity and kindness whatever the outcome.

5. Organ and tissue donation

Choice: I agree to donate

6. Where I wish to be cared for

At home, if possible, with my family nearby.

7. Other wishes

I would like a priest to visit me, and my cat to stay with Claire.

8. Using this directive

  • My doctors and my trusted person should follow this directive as far as the law allows. If a doctor cannot do so in good conscience, they should hand my care to one who can.
  • If a situation is not covered, or if my wishes are unclear, my trusted person decides what I would most probably want, using what I have written here about my values and wishes.
  • I may change or cancel this directive at any time, in writing, or by telling my doctor or trusted person, even if I am ill. The latest one I sign applies. I will review it every few years.
  • I want a copy of this directive kept in my medical file and a copy given to my trusted person, my doctor and my family.
  • Copies are held by: Claire Dubois, Paul Dubois, Dr Anne Moreau and my hospital file at Hôpital Édouard Herriot
  • This directive follows the law of France. If it does not meet a rule of that law, I still want it to be read as a clear statement of my wishes.

My doctor: Dr Anne Moreau, Cabinet Part-Dieu, +33 4 72 00 00 00

Signed at Lyon on 21 November 2026.

Signature: ______________________
Marie Dubois

If I cannot sign, signed for me, in my presence and at my direction, by: ______________________

Witnesses

We confirm that Marie Dubois signed this directive in our presence, freely, and that they appeared to understand it. We are adults. We are not named in it as a trusted person or back-up person, we are not a doctor or carer treating Marie Dubois or an owner or employee of a hospital or care home caring for them, and we do not expect to gain from Marie Dubois's death. At least one of us is not related to Marie Dubois by blood, marriage or adoption.

Witness 1: Hugo Martin, 14 rue Garibaldi, Lyon Signature: ______________________
Witness 2: Sophie Bernard, 3 cours Lafayette, Lyon Signature: ______________________

If the law of France requires a doctor, notary or official

Name and title: ______________________ Signature and stamp: ______________________ Date: __________

Acceptance by my trusted person

I agree to act as trusted person for Marie Dubois, and to speak for their wishes, not my own.

Claire Dubois Signature: ______________________ Date: __________
Back-up person, Paul Dubois, son, +33 6 98 76 54 32: Signature ______________________ Date: __________

Reviews

I have read this directive again, and it still states my wishes.

Date: __________ Signature: ______________________

Templates are a careful starting point, not legal advice. Where the law matters, check what applies where you are.

Personal and family

What this template is for

A living will and advance directive you fill in online: your care wishes, who speaks for you, end of life choices and signatures. Word or PDF, free.

It is free to fill in online, needs no account, and downloads as a Word document or a PDF. See all Personal and family templates

Personal and family

What you fill in

The form asks for 28 details. The document fills itself in as you type.

  • Your full name

    For example: Marie Dubois

  • Date of birth

    For example: 30 April 1958

  • ID, passport or health insurance number (optional)optional

    For example: 2 58 04 69 123 456 78

  • Your address

    For example: 8 rue Victor Hugo, 69003 Lyon, France

  • Trusted person: full name

    The person who speaks for you about your care if you cannot. Ask them first.

    For example: Claire Dubois

  • Relationship

    For example: daughter

  • Their phone and address

    For example: +33 6 12 34 56 78, 5 place Bellecour, Lyon

  • Back-up person, with contact (optional)optional

    For example: Paul Dubois, son, +33 6 98 76 54 32

  • How far your trusted person's decision goes

    For example: They must follow my written wishes below, and decide only what they do not cover.

  • What matters most to you (optional)optional

    Your values help doctors and your trusted person where the choices below do not fit.

    For example: Being at home, recognising my family, not being in pain, and keeping my dignity.

  • Situations in which your choices apply

    One situation per line. Doctors follow a refusal only where the situation matches, so name each one clearly.

    For example: I have an illness that cannot be cured and is expected to cause my death I am permanently unconscious, with no reasonable hope of waking I have severe dementia and can no longer recognise my family

  • Resuscitation if your heart or breathing stops (CPR)

    For example: I do not want this

  • Breathing machine (ventilator)

    For example: Only for a trial period, to be stopped if it does not help

  • Artificial feeding and fluids (tube or drip)

    For example: I do not want this

  • Antibiotics for a life-threatening infection

    For example: My trusted person decides

  • Treatments that only prolong dying, such as dialysis or intensive care

    For example: My trusted person decides

  • Your wishes about treatment in your own words

    Say in which situations it applies, for example terminal illness, permanent loss of consciousness or severe dementia.

    For example: If I have an illness with no hope of recovery, or I permanently cannot recognise my family, I do not want to be kept alive by a machine, but I want my pain and distress treated fully, even if that shortens my life.

  • If you are pregnant (optional)optional

    Leave it empty if it does not apply to you. Some places, such as several US states, limit or set aside a refusal of treatment during pregnancy, whatever you choose.

    For example: I want the treatment needed for the safe birth of my child. After the birth, my choices above apply again.

  • Pain relief and comfort (optional)optional

    For example: Give me whatever medicine is needed to keep me comfortable, even if it makes me sleepy.

  • Organ and tissue donation

    Some countries keep a separate donor register that you must also join or leave.

    For example: I agree to donate

  • Where you wish to be cared for (optional)optional

    For example: At home, if possible, with my family nearby.

  • Other wishes, including spiritual or religious ones (optional)optional

    For example: I would like a priest to visit me, and my cat to stay with Claire.

  • Who holds a copy (optional)optional

    So that the people who need it can find it quickly.

    For example: Claire Dubois, Paul Dubois, Dr Anne Moreau and my hospital file at Hôpital Édouard Herriot

  • Your doctor, with contact (optional)optional

    For example: Dr Anne Moreau, Cabinet Part-Dieu, +33 4 72 00 00 00

  • First witness: name and address

    Often must not be your trusted person, an heir, your doctor or care staff, and at least one often must not be a relative. Some places accept a notary instead. Check local rules.

    For example: Hugo Martin, 14 rue Garibaldi, Lyon

  • Second witness: name and address

    For example: Sophie Bernard, 3 cours Lafayette, Lyon

  • Country or state where you live

    For example: France

  • Place

    For example: Lyon

Personal and family

What is inside

The parts of this document, in order.

  1. 11. The person who speaks for me
  2. 22. What matters most to me
  3. 33. My choices about treatment
  4. 44. Pain relief and comfort
  5. 55. Organ and tissue donation
  6. 66. Where I wish to be cared for
  7. 77. Other wishes
  8. 88. Using this directive
  9. 9Witnesses
  10. 10If the law of Country or state where you live requires a doctor, notary or official
  11. 11Acceptance by my trusted person
  12. 12Reviews

Templates

How it works

  1. 01

    Fill in

    Type your details in the form. The document fills itself in as you type; click any gap to jump to its field.

  2. 02

    Check

    Read it through. Gaps you have not filled stay marked, so nothing goes out half done.

  3. 03

    Download

    Save it as a Word document to edit further, or as a PDF to send or print.

Make it yours with AI

Open it in the chat and ask for changes: shorter, firmer, another situation, another language.

Adapt it with nerix

Personal and family

Questions people ask

What details does this template ask for?

The form asks for 28 details, starting with Your full name, Date of birth, Your address, Trusted person: full name, Relationship. 9 more are optional.

Can I download this template as Word or PDF?

Yes. When you have filled in the form, save it as a Word document to keep editing, or as a PDF to send or print. It is free and needs no account.

Is what I type sent anywhere?

No. What you type stays in your browser while you fill in the document. It only goes to nerix if you choose to open the template in the chat.

What should I check before I use this template?

This is an important document and the law on it differs a lot between countries and even between states. Whether it is binding or only guidance for doctors, who may be your trusted person, how many witnesses you need (and who may not be one), and whether a doctor, a notary or an official register must be involved all depend on where you live. Some places require their own official form, or do not accept a document made elsewhere. In some places your trusted person can decide for you only if you also sign a separate power of attorney for health, often on an official form and registered; otherwise they can only tell doctors what you would want. Some treatments you may wish to refuse, and some you may not ask for, are limited by law. Talk it through with your doctor and your family, ask a lawyer or a patient organisation if you can, and review it every few years. This template is not medical or legal advice and cannot promise that your wishes will be followed.

Are these personal letter templates free?

Yes. Each one is free to fill in and download as Word or PDF, with no account.

Will an office accept an authorization letter?

Many do, often with a copy of your ID. Some have their own form, so ask the office first. For property or court matters you may need a notarised power of attorney.

Does a child travel consent letter work for every border?

Rules differ by country and airline. Check what the destination and the airline ask for, and bring ID copies and contact details for both parents.

Who should sign the letter?

The person giving the consent or statement, with the date. Some offices also want a witness or a notary, so ask before you rely on it.